
Zepbound Patient Journey
Zepbound Dosing Schedule: A Week-by-Week Patient Journey Guide
The Zepbound dosing schedule is a four-week-per-step titration: start at 2.5mg weekly, step up by 2.5mg every four weeks, and land on a maintenance dose of 5mg, 10mg, or 15mg. The full schedule reaches the 15mg maximum at roughly week 21, but most patients stop earlier once weight loss meets their goal. This guide maps the journey week-by-week instead of as a static table, so you know what phase you are in, what decision is next, and what the FDA label allows at each step.
If you want the dose-by-step lookup table instead, see the Zepbound dosage chart. For the full compound-wide clinical context, see the complete tirzepatide dosing guide. This page is part of the Tirzepatide hub.
Key Takeaways
- Starting dose is 2.5mg once weekly for four weeks. This is a tolerance step, not a therapeutic dose. Meaningful weight loss begins at the first 5mg step.
- Titration interval is every four weeks in 2.5mg increments through the sequence 2.5 to 5 to 7.5 to 10 to 12.5 to 15mg, reaching the maximum dose at approximately week 21.
- Maintenance doses are 5mg, 10mg, or 15mg. The 2.5mg, 7.5mg, and 12.5mg strengths are titration steps only and are not intended for long-term maintenance per the FDA label.
- Missed dose rule: inject within 4 days (96 hours) of the scheduled time, or skip and resume the next week. Never take two doses within 72 hours of each other.
- You can stay at 5mg or 10mg indefinitely if weight loss goals are met and tolerability is good. Escalation is optional, not mandatory. Track drug levels week by week with the free Zepbound pharmacokinetic calculator.
2.5mg
Starting dose for weeks 1 through 4
4 weeks
Standard interval between every titration step
15mg
Maximum approved weekly dose
~20 weeks
Time from start to maximum dose at standard pace
What "Zepbound Dosing Schedule" Means for Patients
A dosing schedule is the calendar view of treatment, not the dose lookup table. The lookup table answers "what is dose X" in a single row. The schedule answers "what week am I in, what comes next, and what choice do I have at each milestone." Both are useful for different questions. If you already know your current dose and only need a per-step reference, the Zepbound dosage chart is the right page. This page is for patients walking through the schedule end-to-end.
The schedule on this page is strictly the FDA-approved Zepbound brand: the single-use KwikPen autoinjector across six pen strengths, plus the brand-name single-dose vial. Everything below comes from the Zepbound prescribing information (Section 2.1 Dosage Escalation Schedule and Section 2.4 Administration). The same titration applies to both the chronic weight management indication (FDA approval November 2023) and the obstructive sleep apnea indication added December 2024.
Zepbound's Six Pen Strengths and Three Maintenance Tiers
Zepbound is supplied as six fixed pen strengths. Three of those are maintenance doses, three are titration-only steps. The distinction is set by the FDA label and is the single most important fact in the whole schedule.
| Pen Strength | Role | Maintenance Eligible? |
|---|---|---|
| 2.5 mg | Starting dose (weeks 1 to 4) | No (titration only) |
| 5 mg | First therapeutic dose (weeks 5 to 8) | Yes |
| 7.5 mg | Titration step (weeks 9 to 12) | No (titration only) |
| 10 mg | Second therapeutic dose (weeks 13 to 16) | Yes |
| 12.5 mg | Titration step (weeks 17 to 20) | No (titration only) |
| 15 mg | Maximum dose (week 21 onward) | Yes |
Source: Zepbound Prescribing Information, Section 2.1. The 2.5/7.5/12.5mg strengths exist for tolerance bridging between maintenance tiers and are not approved for indefinite weekly use.
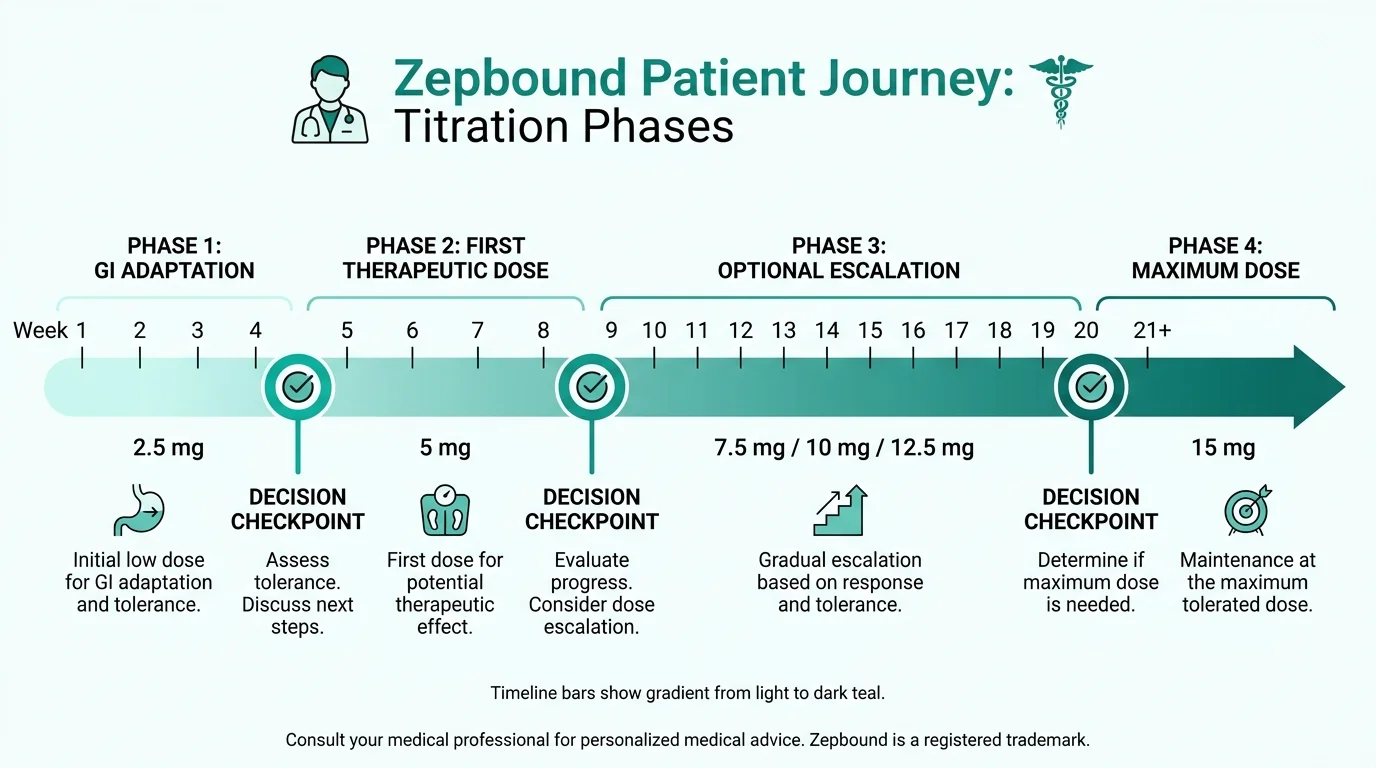
The Zepbound titration arc: four phases, three decision checkpoints, and a maximum dose reached around week 21 for patients who escalate all the way.
See Your Zepbound Drug Levels Week by Week
Pick any dose and any titration plan. The free pharmacokinetic calculator plots tirzepatide accumulation across the full schedule so you can see exactly where steady state lands at every step.
Open Free CalculatorPhase 1, Weeks 1 to 4: The 2.5 mg Tolerance Phase
Weeks one through four are the tolerance phase. The 2.5mg dose is intentionally sub-therapeutic. Its purpose is to let your gastrointestinal system adapt to a GIP and GLP-1 agonist before the first therapeutic dose starts at week five. Mild appetite suppression is normal during this phase. Some patients see a small initial drop in weight, but the trial data do not show meaningful weight loss at 2.5mg by design.
Gastrointestinal effects (nausea, mild abdominal discomfort, occasional loose stools) typically peak in the first 2 to 4 days after each weekly injection and settle by week three. If symptoms are significant rather than mild, your prescriber can hold you at 2.5mg for an additional four weeks before escalating, per the label. The deeper symptom-by-dose breakdown is in the Zepbound side effects guide.
Is 2.5 mg Enough to Lose Weight?
Not meaningfully, no. The 2.5mg dose is below the therapeutic threshold for weight reduction. In the SURMOUNT-1 anchor trial, the lowest therapeutic dose arm was 5mg, which produced approximately 15% mean body weight loss at 72 weeks. The 2.5mg dose was used only as a four-week run-in step before randomization to a maintenance dose. Expect minimal weight change in weeks one through four; the goal of this phase is tolerance, not loss.
Phase 2, Weeks 5 to 8: The First Therapeutic Dose (5 mg)
Week five is the first therapeutic checkpoint. The 5mg pen is the lowest dose that produced clinically meaningful weight loss in the trial program. In SURMOUNT-1, the 5mg maintenance arm averaged approximately 15% body weight reduction at 72 weeks. Many patients will be satisfied with this outcome and stay on 5mg indefinitely. Escalation to higher doses is optional, not mandatory.
Gastrointestinal effects often return briefly at this first dose increase, peaking days 2 to 4 after the first 5mg injection and settling over two to four weeks. By the end of week eight you reach the first maintenance decision: stay at 5mg, or escalate to 7.5mg as a tolerance step on the way to 10mg.
5 mg Maintenance Decision (end of week 8)
Stay at 5 mg if: weight loss is on track for your goal, side effects are tolerable, and you and your prescriber agree no further escalation is needed.
Escalate to 7.5 mg if: weight loss has plateaued below your goal, you are tolerating 5 mg well, and your prescriber assesses additional benefit is likely. The 7.5 mg step is bridging only, not a destination.
Phase 3, Weeks 9 to 20: Optional Escalation (7.5 to 10 to 12.5 mg)
Phase three covers the optional escalation arc. The 7.5mg pen (weeks 9 to 12) is a bridge to 10mg, and the 12.5mg pen (weeks 17 to 20) is a bridge to 15mg. Neither is a maintenance dose under the FDA label. The 10mg pen (weeks 13 to 16) is the second therapeutic checkpoint. In SURMOUNT-1, the 10mg maintenance arm averaged approximately 19.5% body weight reduction at 72 weeks, roughly 4.5 percentage points more than the 5mg arm over the same period.
Two questions come up frequently in this phase. The first is whether escalation is required after each step. It is not. Per the prescribing information, you can stay at any maintenance dose (5mg, 10mg, or 15mg) once you reach it, as long as your prescriber agrees that the dose is meeting your treatment goals. The second is why the schedule includes odd-numbered doses at all. The 2.5mg increments exist to ease gastrointestinal tolerance; jumping directly from 5mg to 10mg or 10mg to 15mg produces more nausea than walking through the half-step.
The 10 mg Maintenance Decision
End of week 16 is the second maintenance checkpoint. By this point you have data on what your body does on a higher therapeutic dose, and you and your prescriber can decide whether 10mg meets the goal or whether continuing to 12.5mg (a four-week bridge) and then 15mg is worth the trade-off.
10 mg Maintenance Decision (end of week 16)
Stay at 10 mg if: weight loss is meeting your goal, side effects are stable or improving, and the SURMOUNT-1 ~19.5% trajectory is acceptable.
Escalate to 12.5 mg if: weight loss has plateaued below your goal at 10 mg, you are tolerating 10 mg well, and additional reduction is the treatment objective. 12.5 mg is bridging only; the next maintenance tier is 15 mg.
Phase 4, Week 21+: Maximum Dose (15 mg) and Long-Term Maintenance
Week 21 is when patients who escalate all the way reach the 15mg maximum. In SURMOUNT-1, the 15mg maintenance arm averaged 20.9% mean body weight reduction at 72 weeks, the largest mean loss observed in the trial. Not every patient reaches 15mg, and not every patient should. Roughly half of trial completers met their treatment goal at 5mg or 10mg and did not escalate further in clinical practice.
For long-term maintenance, the FDA label does not define an upper time limit on treatment. Tirzepatide is approved for chronic weight management, meaning treatment continues as long as the indication is met and the patient and clinician agree to continue. Discontinuation studies show weight regain is common when treatment stops, so the schedule on this page is best viewed as a long-arc plan rather than a finite course. For the outcomes data underlying this decision, see Zepbound weight loss results.
Video: Tirzepatide Titration and Dosing Walkthrough
A clinical walkthrough of the tirzepatide titration schedule covering each dose step, the four-week interval, and when to consider holding or escalating. The medication discussed is the same molecule as Zepbound; the schedule applies identically.
Missed Dose Rules
Missed doses happen. The FDA label gives a precise rule that depends on how much time has passed since the scheduled injection.
- Within 4 days (96 hours) of the missed dose: inject as soon as possible and resume your regular weekly schedule on the same day next week.
- More than 4 days after the missed dose: skip the missed dose entirely. Take your next dose on the regular scheduled day.
- Two-dose rule: never take two doses within 72 hours of each other. This is a hard floor on dose spacing regardless of any other circumstance.
Do Not Double-Dose
Doubling up to "catch up" after a missed dose is not safe. Tirzepatide has a half-life of approximately 5 days, so back-to-back injections stack drug levels and significantly increase nausea, vomiting, and dehydration risk. The skip-and-resume rule is the correct response when more than 96 hours have passed.
Changing Your Injection Day
If you want to move your weekly injection to a different day (work travel, scheduling conflict, weekend preference), the rule is the same as the two-dose rule. You can shift the day as long as there are at least 72 hours (3 days) between your most recent dose and the new scheduled day. After the one-time shift, continue weekly on the new day.
Managing the Titration: Practical Patient Guidance
A few practical points apply across every titration step and are easy to lose sight of when focusing on the dose number alone.
- Gastrointestinal symptom timing: at each new dose, expect symptoms to peak days 2 to 4 and settle over two to four weeks. Patterns from prior steps usually repeat at the next step but rarely worsen materially.
- Holding a step: if a step produces significant side effects, your prescriber can extend that step by an additional four weeks before escalating. This is built into the FDA label, not a workaround.
- Steady state: drug levels at any given dose reach steady state in approximately 4 weeks (Zepbound label). This is why the titration interval is four weeks rather than two; the body needs that long to fully equilibrate at each new dose.
- Injection timing within the week: any time of day, with or without food, but consistent day-to-day. Pick a day that fits your routine and stay with it.
- Injection site: abdomen, thigh, or upper arm, rotating between weekly injections. See the Zepbound injection sites guide for site selection and rotation patterns.
How the Zepbound Calculator Helps Track Your Schedule
Tirzepatide has a half-life of approximately 5 days, which means drug levels build up gradually over about 4 weeks at each new dose before flattening at steady state. The free pharmacokinetic calculator plots this accumulation across your full titration schedule. You can see exactly where your levels are in week three of the 5mg step, how steady state shifts when you move to 10mg, and what happens to levels during a hold step or after a missed dose. It is the visual companion to this schedule.

The maintenance decision is the same shape at every checkpoint: meet goal and tolerate well, stay; plateau below goal and tolerate well, escalate.
Maintenance Dose Decision Criteria
The maintenance decision at every checkpoint comes down to two questions: is the current dose meeting the weight loss goal, and is tolerability acceptable. Both have to land on "yes" to stay; either landing on "no" pushes the decision toward escalation or, in the tolerability case, toward holding the step longer.
The FDA label explicitly permits indefinite maintenance at 5mg or 10mg, not just at 15mg. This is worth restating because the assumption that "more dose equals better outcome" is built into a lot of GLP-1 discussion online. The trial data show diminishing returns at higher doses for many patients, and the side-effect burden trends upward with dose. Staying at 5mg or 10mg if those doses meet the goal is the right call, not a compromise.
Cost is a secondary consideration. Through the LillyDirect self-pay program, the monthly price of Zepbound varies by dose tier. The Zepbound cost guide covers the full tier-by-tier breakdown, and the LillyDirect Zepbound program page covers eligibility and ordering. The cost difference between maintenance tiers should not drive the medical decision, but it is a fact patients factor in.
Frequently Asked Questions About the Zepbound Dosing Schedule
How long do you stay on 2.5 mg Zepbound?
The standard period is 4 weeks. The 2.5mg dose exists to help your gastrointestinal system adjust before the first therapeutic dose (5mg) begins at week 5. If side effects are significant, your prescriber may hold 2.5mg for an additional 4 weeks before escalating, per Section 2.1 of the Zepbound prescribing information.
Is 2.5 mg Zepbound enough to lose weight?
Not meaningfully. The 2.5mg dose is intentionally sub-therapeutic and exists for gastrointestinal tolerance, not for weight loss. In SURMOUNT-1, meaningful weight loss began at the 5mg maintenance dose, which averaged approximately 15% body weight reduction at 72 weeks. Expect minimal weight change during weeks 1 to 4.
Do I have to keep escalating my Zepbound dose?
No. Escalation past 5mg or 10mg is optional. The FDA prescribing information names 5mg, 10mg, and 15mg as maintenance doses. If you are meeting your weight loss goals and tolerating the current dose well, your prescriber may keep you at that dose indefinitely. Higher dose does not automatically mean better outcome.
What is the Zepbound maintenance schedule?
After completing titration, you stay on your maintenance dose (5mg, 10mg, or 15mg) once weekly, indefinitely, as long as treatment is indicated. The 2.5mg, 7.5mg, and 12.5mg strengths are titration steps only and are not approved as long-term maintenance doses per the FDA label.
What if I miss a Zepbound dose?
If fewer than 4 days (96 hours) have passed since your scheduled dose, inject as soon as possible and resume your regular weekly schedule. If more than 4 days have passed, skip the missed dose and take your next dose on the regular scheduled day. Never take two doses within 72 hours of each other.
How long does it take to reach the maximum Zepbound dose?
At the standard titration pace (one 2.5mg increase every 4 weeks), it takes approximately 20 weeks to reach the 15mg maximum dose. Many patients stay at an intermediate maintenance dose (5mg or 10mg) and never reach 15mg, which is entirely appropriate if weight loss goals are met at the lower dose.
How much weight can you lose on Zepbound in 6 months?
In SURMOUNT-1, patients on the 15mg arm were still mid-titration at the 6-month mark (approximately week 20 to 24), so most had not yet reached the maintenance dose. Weight loss at 6 months varies by individual response and dose tier. The trial's headline 20.9% mean body weight reduction was measured at 72 weeks (roughly 17 months), not 6 months.
Can I change the day of the week I take Zepbound?
Yes. You can change your injection day as long as there are at least 3 days (72 hours) between your previous dose and the new scheduled day. After the one-time adjustment, continue weekly injections on the new day. This rule comes from the Zepbound Medication Guide and is a hard floor on dose spacing.
What happens to Zepbound drug levels during titration?
Tirzepatide has a half-life of approximately 5 days. Drug levels accumulate over about 4 weeks at each dose until reaching steady state. The free Zepbound pharmacokinetic calculator visualizes this accumulation across your full titration schedule so you can see exactly where levels are week by week, including hold steps and missed-dose scenarios.
Plot Your Full Zepbound Schedule
Enter your starting date, planned titration pace, and target maintenance dose. The free tirzepatide calculator shows your drug-level curve across the full schedule, including steady-state checkpoints at every step.
Open Free CalculatorReferences
- Eli Lilly and Company. ZEPBOUND (tirzepatide) injection, for subcutaneous use. Full Prescribing Information. FDA NDA 217806. Updated February 2025. accessdata.fda.gov (Zepbound 2025 label PDF). (Primary FDA source: Section 2.1 Recommended Dosage Escalation Schedule, Section 2.4 Important Administration Instructions, maintenance dose definition, missed-dose rule, and OSA dosing parity.)
- Jastreboff AM, Aronne LJ, Ahmad NN, et al. Tirzepatide Once Weekly for the Treatment of Obesity. New England Journal of Medicine. 2022;387(3):205-216. DOI: 10.1056/NEJMoa2206038. (SURMOUNT-1 anchor trial: ~15% mean body-weight reduction at 5mg, ~19.5% at 10mg, and 20.9% at 15mg over 72 weeks; titration protocol identical to FDA label.)
- Eli Lilly and Company. ZEPBOUND Medication Guide. FDA-approved patient labeling. 2023. pi.lilly.com (Zepbound Medication Guide). (Patient-facing labeling: day-change rule (minimum 72 hours between any two doses), injection instructions, and patient missed-dose guidance.)
- Eli Lilly and Company. ZEPBOUND HCP Dosage Page. Healthcare Provider Reference. zepbound.lilly.com/hcp/dosage. (HCP-facing summary of dose escalation schedule, used as a cross-check on the patient-journey framing.)
- U.S. Food and Drug Administration. ZEPBOUND (tirzepatide) injection - February 2025 Label Update. accessdata.fda.gov (FDA label history). (Confirms identical titration schedule for the chronic weight management indication and the obstructive sleep apnea indication added December 2024.)
Medical Disclaimer
This article is for informational purposes only and does not constitute medical advice. All dosing values, titration timing, missed-dose rules, and maintenance-dose definitions on this page reflect the FDA-approved Zepbound (tirzepatide) prescribing information (NDA 217806, updated February 2025) and the SURMOUNT-1 trial outcomes data. The titration schedule on this page is the standard FDA-recommended pace; your prescriber may modify the pace, hold a step longer, or stop at an intermediate maintenance dose based on your individual response and tolerability. Always follow the schedule your prescriber gives you. GLP3Planner is an informational and calculation tool, not a medical service.
More Zepbound and Tirzepatide Guides on GLP3Planner
Zepbound Dosage Chart
Static dose-by-step reference: every Zepbound pen strength with weight loss data and missed-dose rules in one table.
Complete Tirzepatide Dosing Guide
Compound-wide protocol covering mechanism, clinical context, and both Mounjaro and Zepbound brand variants.
Zepbound Side Effects Guide
What to expect at each titration step, peak symptom timing, and management strategies for common gastrointestinal effects.
Zepbound Cost Guide
Price breakdown by dose tier across pen and single-dose vial formulations, including the LillyDirect self-pay program.