
Visual Reference
Microdosing Tirzepatide Chart: Week-by-Week Dose Reference
This is the scannable companion to our full microdosing tirzepatide guide. Below you get a clean microdosing tirzepatide chart for twice-weekly and three-times-weekly split schedules, the IU conversion math at common vial concentrations, and an off-label sub-2.5mg reference. Every number is derived from the FDA-approved dose ladder. No clinical trial has studied split-dose tirzepatide directly, so treat this as a planning reference, not a prescription.
Key Takeaways
- Half-life is about 5 days (120 hours). That shorter half-life is why tirzepatide swings more between weekly injections than semaglutide, and part of why some people split the dose.
- Steady state takes about 4 weeks (Mounjaro and Zepbound labels). Splitting the weekly dose does not change how long it takes to reach stable drug levels.
- Standard FDA start is 2.5 mg once weekly. Every split number in the chart is the standard dose divided by injection frequency, nothing more.
- Sub-2.5mg starts are off-label. No published SURMOUNT or SURPASS trial tested a tirzepatide dose below 2.5 mg.
- This chart is a reference, not a protocol. Talk to your prescriber before changing how you dose.
~5 days
Tirzepatide Half-Life (120 hours)
4 to 5 wks
Time to Steady State
2.5 mg
FDA-Approved Starting Dose
15 mg
Maximum Approved Dose
What Is the Standard Tirzepatide Titration vs Microdosing?
If you landed here from a standard-dosing search, start with this. The FDA-approved protocol and the microdosing approach use the same drug but distribute it very differently. The table below sets the two side by side.
| Dimension | Standard Titration | Microdosing |
|---|---|---|
| Dose ladder | 2.5mg → 5mg → 7.5mg → 10mg → 12.5mg → 15mg, every 4 weeks | Same weekly mg, split across 2 or 3 injections, or a sub-standard start |
| Frequency | Once weekly | Twice or three times weekly |
| Evidence base | SURMOUNT-1 (72 weeks, 20.9% mean weight loss at 15mg) | No direct clinical trial; pharmacokinetic modeling only |
| Device | Single-dose KwikPen at fixed strengths | Compounded vial plus syringe (pens cannot split below their fixed dose) |
Standard titration per the FDA Mounjaro and Zepbound prescribing information; SURMOUNT-1 weight-loss figure per Jastreboff et al., NEJM 2022.
For the standard, non-split schedule on its own, see our tirzepatide dosage chart. This page is only about the split and microdose variants.
Why Users Microdose Tirzepatide
Two reasons show up over and over in real-world use. The first is tolerability. A weekly injection produces a single concentration peak; splitting it into two smaller injections lowers that peak. Our calculator's pharmacokinetic model shows a roughly 15% lower steady-state peak with a Monday/Thursday split, which is the usual motivation for people fighting nausea. The second reason is cost. A lower total weekly dose, or stretching a compounded vial, reduces monthly spend.
Important: No Tier 1 clinical trial has studied sub-2.5mg tirzepatide efficacy or safety, and no trial has directly studied split-dose tirzepatide. This is off-label use. The numbers below are arithmetic from the FDA dose ladder, not studied microdose levels.
Model Any Split Schedule Before You Commit
The free pharmacokinetic calculator shows peak, trough, and steady-state levels for any tirzepatide dose, frequency, and vial concentration you enter.
Open Tirzepatide Calculator →Microdosing Tirzepatide Chart: Split-Dose Schedules
This is the core reference. Each split value is the standard FDA-approved weekly dose divided by the number of injections. The IU column assumes a 10mg/mL vial concentration, where 1 mL equals 100 IU on a standard U-100 insulin syringe. Concentration varies by pharmacy, so confirm yours before using these IU figures.
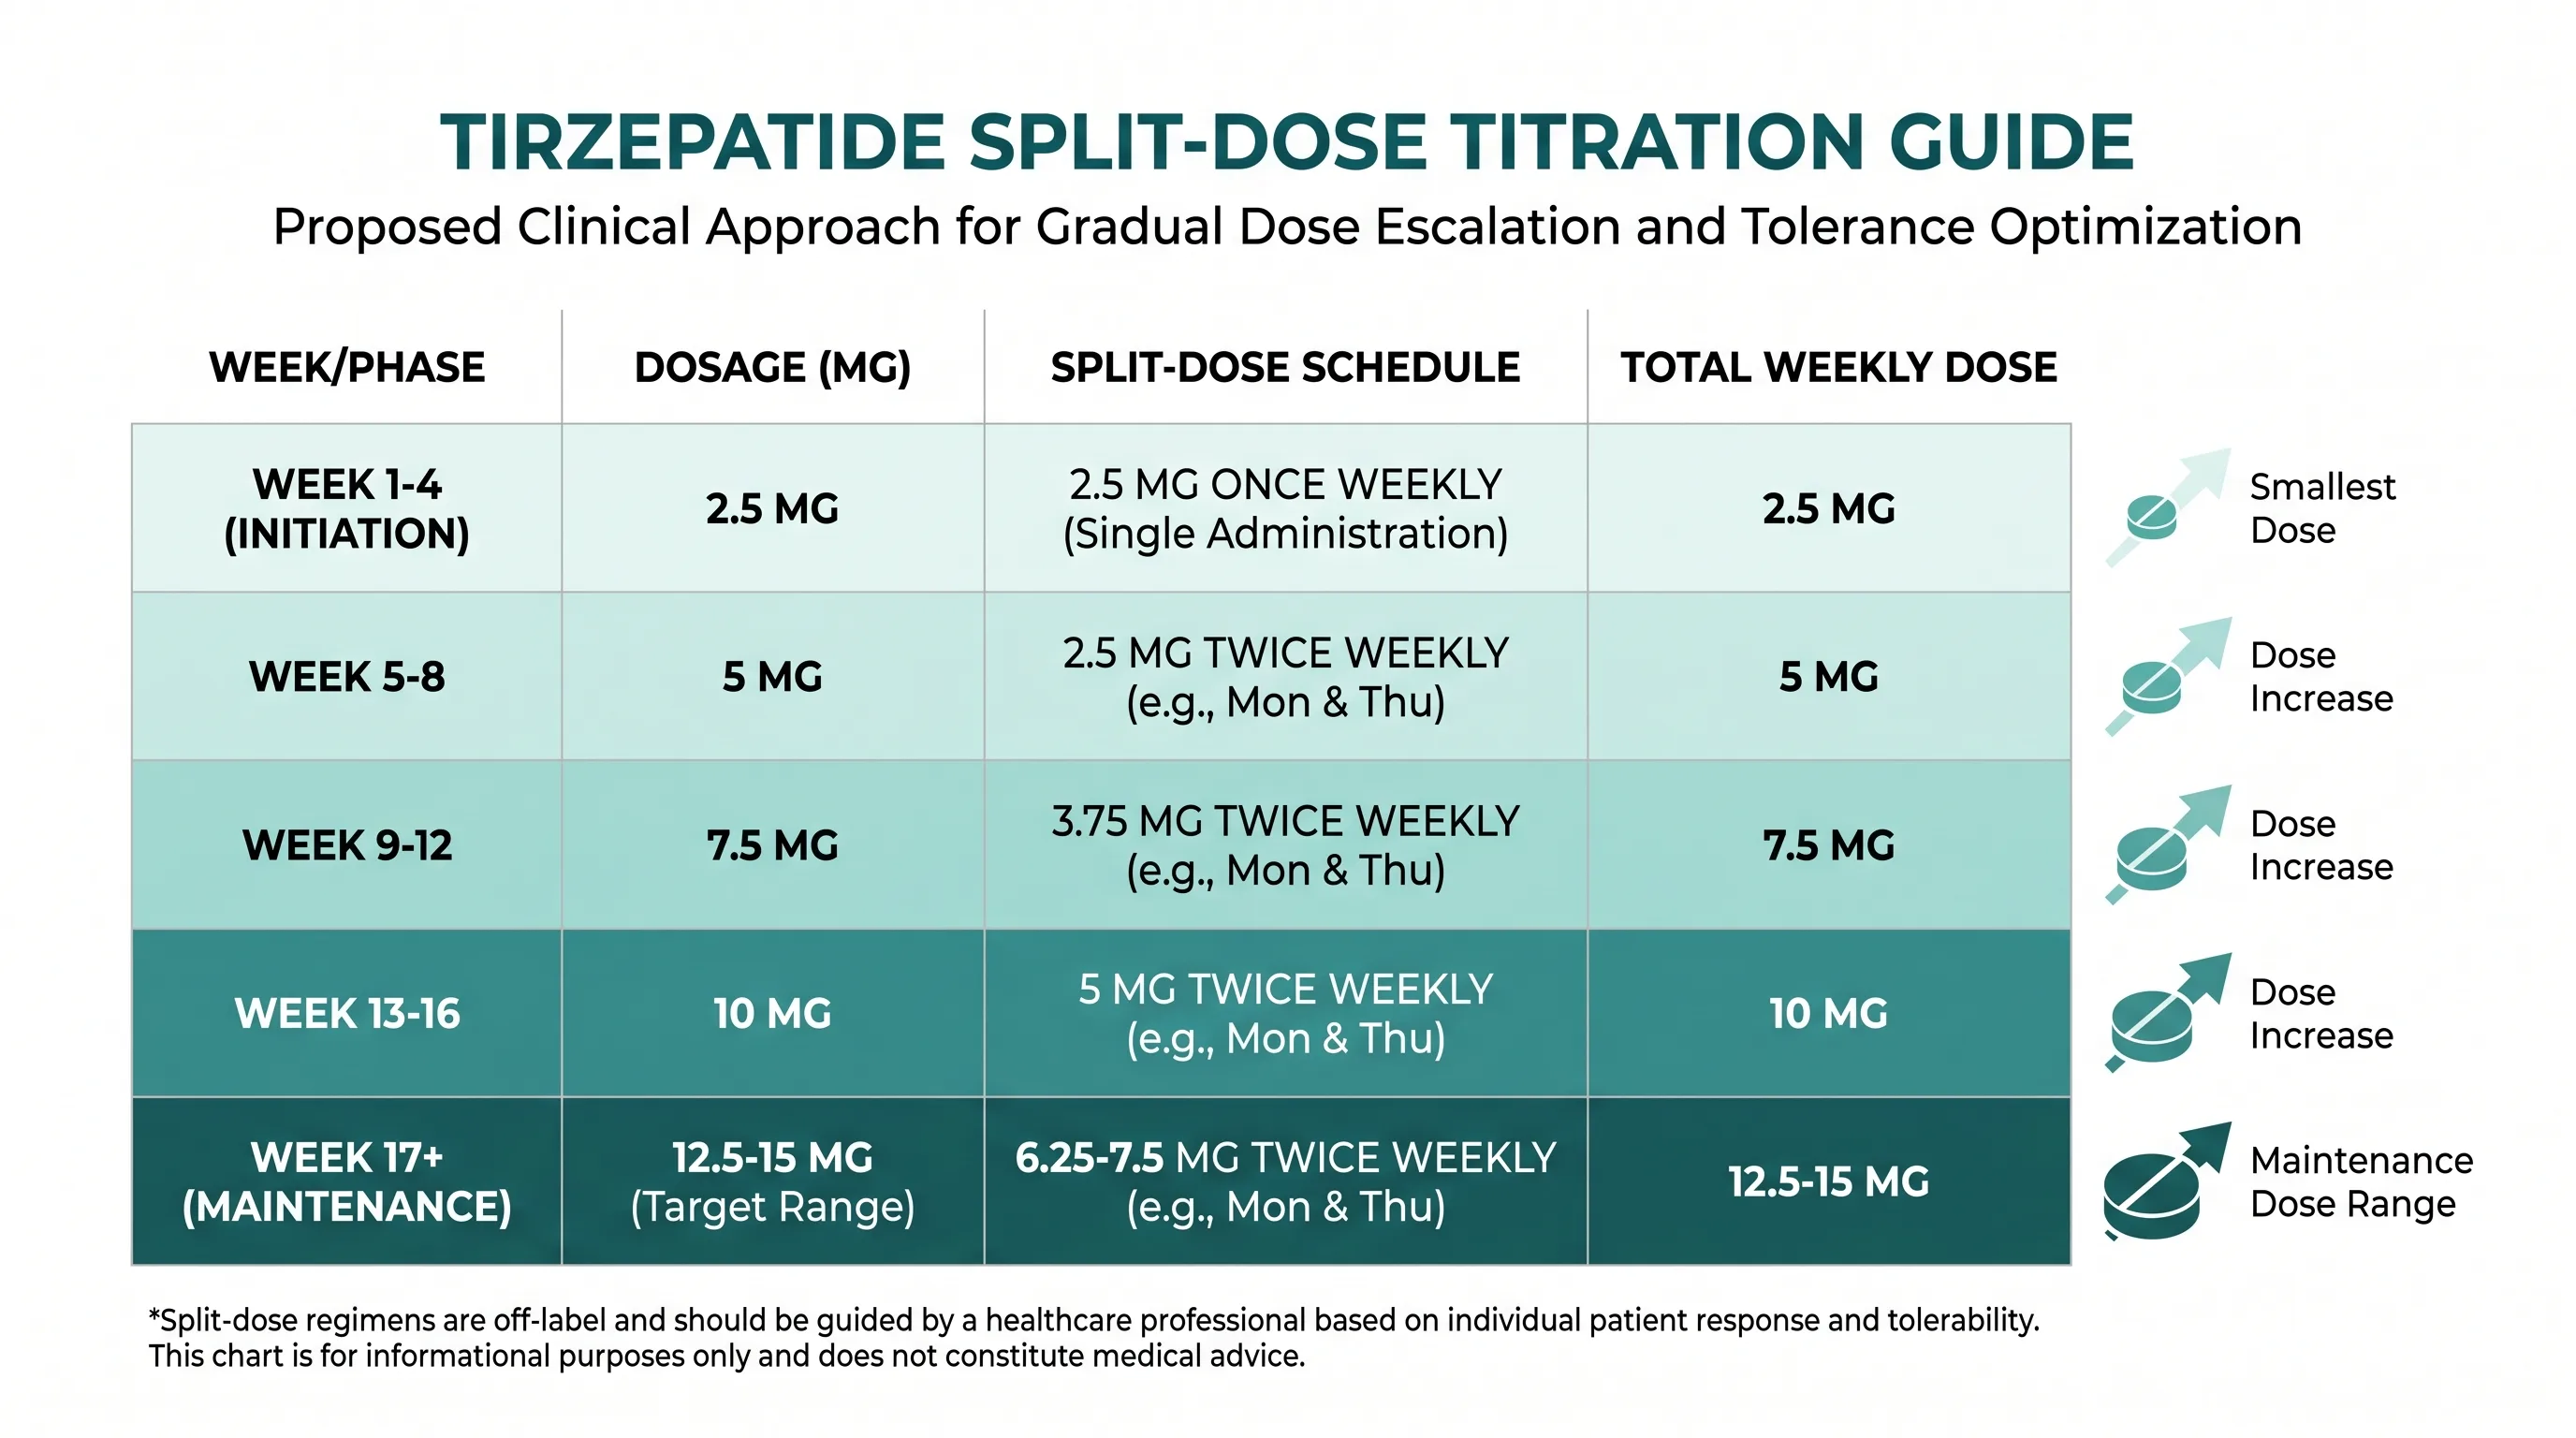
Twice-weekly split-dose values derived from the FDA tirzepatide dose ladder. IU shown at 10mg/mL.
Chart A: Twice-Weekly Split Dose (Monday and Thursday)
The most common split. The standard weekly dose is divided in two, injected on Monday and Thursday (or any 3-to-4-day spacing).
| Week Range | Standard Dose | Split Dose (per injection) | IU at 10mg/mL | Phase |
|---|---|---|---|---|
| Weeks 1 to 4 | 2.5 mg | 1.25 mg | 12.5 IU | Initiation |
| Weeks 5 to 8 | 5 mg | 2.5 mg | 25 IU | Escalation 1 |
| Weeks 9 to 12 | 7.5 mg | 3.75 mg | 37.5 IU | Escalation 2 |
| Weeks 13 to 16 | 10 mg | 5 mg | 50 IU | Escalation 3 |
| Weeks 17 to 20 | 12.5 mg | 6.25 mg | 62.5 IU | Escalation 4 |
| Weeks 21+ | 15 mg | 7.5 mg | 75 IU | Maximum |
Note: IU values assume 10mg/mL concentration, where 1 mL is 100 IU. Concentration varies by compounding pharmacy. Always verify with your provider before drawing a dose.
A Monday/Thursday split lowers the modelled steady-state peak by roughly 15% while keeping weekly drug exposure the same, per the pharmacokinetic modeling in our microdosing tirzepatide guide. No clinical trial has directly studied split-dose efficacy.
Chart B: Three-Times-Weekly Split Dose (Mon, Wed, Fri)
The same weekly mg split across three injections. The pharmacokinetic case for it is stronger with tirzepatide than with semaglutide, because tirzepatide's shorter half-life gives splitting more to smooth.
| Week Range | Standard Dose | Split Dose (per injection) | IU at 10mg/mL |
|---|---|---|---|
| Weeks 1 to 4 | 2.5 mg | 0.83 mg | 8.3 IU |
| Weeks 5 to 8 | 5 mg | 1.67 mg | 16.7 IU |
| Weeks 9 to 12 | 7.5 mg | 2.5 mg | 25 IU |
| Weeks 13 to 16 | 10 mg | 3.33 mg | 33.3 IU |
Tirzepatide has a shorter half-life than semaglutide, about 5 days versus roughly 7, so splitting smooths its curve more (about 19% lower modelled peak for Monday/Wednesday/Friday, against about 11% for semaglutide). For most people the extra smoothing past twice-weekly is small relative to the added injection burden.
Chart C: Sub-Threshold Starts (Below the FDA 2.5mg Dose)
Off-label, no Tier 1 clinical trial evidence. These doses have not been studied in any trial. The lowest tirzepatide dose evaluated in any published SURMOUNT or SURPASS trial is 2.5 mg. Prescribing below 2.5 mg is off-label. Always consult your physician.
Some clinicians begin below 2.5 mg for highly sensitive patients. These values reflect what appears in clinical-practice writing and real-world reports, not trial data. They are shown so you can recognize the range, not as an endorsement of any specific number.
| Week | Dose (mg) | IU at 10mg/mL | Notes |
|---|---|---|---|
| 1 to 2 | 0.5 | 5 IU | Off-label, not studied |
| 3 to 4 | 1.0 | 10 IU | Off-label, not studied |
| 5 to 8 | 1.5 | 15 IU | Off-label, not studied |
| 9+ | 2.5 | 25 IU | FDA-approved start |
How to Read the Chart: IU Conversion Explained
The IU column only works if your vial concentration matches the chart's assumption. Many readers do not know their concentration off the top of their head, which is exactly where dosing errors creep in. The formula is straightforward:
IU = (desired dose in mg ÷ concentration in mg/mL) × 100
Here is the same 2.5 mg per-injection target at three common concentrations, so you can see how much the IU figure moves:
| Desired Dose | Concentration | Volume | IU on U-100 Syringe |
|---|---|---|---|
| 2.5 mg | 5 mg/mL | 0.50 mL | 50 IU |
| 2.5 mg | 10 mg/mL | 0.25 mL | 25 IU |
| 2.5 mg | 20 mg/mL | 0.125 mL | 12.5 IU |
The same 2.5 mg target needs four times the volume at 5mg/mL versus 20mg/mL. Concentration is everything.
For where these vials come from and why concentrations differ, see compounded tirzepatide. To skip the arithmetic entirely, the tirzepatide calculator handles any concentration you type in.
Concentration Varies by Pharmacy
Do not assume. Compounded tirzepatide vials commonly range from 5mg/mL to 20mg/mL depending on the pharmacy. The same IU on two different vials can mean very different milligram doses. Confirm your concentration in writing, and let the calculator at /tirzepatide-calculator do the conversion.
Microdosing Tirzepatide and the Half-Life Factor
Tirzepatide has a half-life of approximately 5 days (120 hours). Semaglutide sits closer to 7 days. That gap matters for split dosing. A shorter half-life means the drug clears faster between weekly injections, so once-weekly tirzepatide produces a larger swing between its peak and its trough than once-weekly semaglutide does. Splitting the dose narrows that swing, which is why the split-dose argument is, if anything, slightly stronger for tirzepatide than for semaglutide.

Once-weekly dosing produces a single high peak; a twice-weekly split produces two lower peaks with less variation.
Two things do not change when you split. First, steady state is still reached at about 4 weeks regardless of how you distribute the weekly dose, because that timeline is driven by the half-life, not the injection schedule. Second, the total weekly exposure stays the same as standard dosing as long as the weekly milligram total is unchanged. What changes is the shape of the curve between injections, not the area under it.
The exact peak-to-trough ratio for each schedule depends on your schedule and your individual absorption and clearance. The figures above are modelled at steady state for standard schedules, and no clinical trial has confirmed them. To see your own case, model it. See the full pharmacokinetic analysis in the microdosing tirzepatide guide, and run your own numbers in the tirzepatide calculator.
Watch: Split-Dose Mechanics Step by Step
Board-certified physician Dr. G walks through the practical mechanics of splitting a GLP-1 dose, including tirzepatide vials. This pairs well with the charts above if you want to see the technique rather than just the numbers.
Who Is Microdosing Tirzepatide For?
Three profiles come up most often in real-world use. None of them is a clinical recommendation; each one is a description of who tends to ask about this approach.
- New starters with high GI sensitivity. People who could not tolerate even the 2.5 mg initiation dose without significant nausea sometimes ask about a gentler on-ramp.
- Weight-maintenance phase. Someone who has hit their goal and wants the lowest dose that holds it, rather than staying at a full maintenance dose.
- Compounded-vial users managing cost. A vial plus syringe makes splitting practical, and stretching a vial reduces monthly spend.
Maintenance use case: Of these, the lowest-effective-dose maintenance approach is the one clinicians discuss most, often as part of a slow taper rather than abrupt discontinuation. It still requires prescriber oversight and the same monitoring as standard dosing.
One thing holds across all three: talk to your prescriber before changing any schedule. The chart is a planning aid, not a green light.
Frequently Asked Questions
What amount is a microdose of tirzepatide?
There is no universally agreed definition. In common usage it means either splitting the standard weekly dose (for example, 2.5 mg into two 1.25 mg injections) or starting below the FDA-approved 2.5 mg threshold. No clinical trial has studied sub-2.5mg tirzepatide. Always consult your prescribing physician before changing your schedule.
Can I lose weight by microdosing tirzepatide?
SURMOUNT-1 showed 20.9% mean body weight loss at the full 15 mg dose over 72 weeks. Lower doses produced less effect, and sub-2.5mg doses were not studied. Some people report weight loss at split or below-standard doses, but clinical evidence for efficacy at microdose levels is currently absent.
Is 2.5 mg of tirzepatide enough to lose weight?
The 2.5 mg dose is the FDA-approved starting dose, intended for tolerability during the first 4 weeks before escalation to 5 mg. SURMOUNT-1 showed dose-dependent weight loss, with higher doses producing larger effects. Some people see meaningful appetite reduction at 2.5 mg, but it is a titration step, not a maintenance dose.
How much tirzepatide per week for microdosing?
The twice-weekly split divides the standard weekly amount into two equal injections. If prescribed 2.5 mg weekly, each injection is 1.25 mg, on Monday and Thursday. The total weekly milligram amount stays the same as standard dosing; only the per-injection dose and frequency change.
What is a microdose of tirzepatide?
A microdose typically refers to a dose below, or split from, the standard FDA-approved weekly amount. Vial-based compounded tirzepatide is required to split below the lowest pen increment. The smallest FDA-labeled tirzepatide dose is 2.5 mg per week, delivered by Mounjaro and Zepbound pens.
How long can I stay on 2.5mg tirzepatide?
The FDA-approved protocol keeps you at 2.5 mg for a minimum of 4 weeks before increasing to 5 mg. There is no fixed upper time limit at any dose; escalation is driven by tolerability and response. Some prescribers keep patients at lower doses longer if weight goals are being met. This is a clinical decision for your provider.
Can I lose weight microdosing tirzepatide at split doses?
Dose-dependent effects are well established in SURMOUNT-1: lower doses produced less weight loss than higher ones. Whether a below-standard dose produces meaningful weight loss depends on individual response. The calculator can model expected active drug levels at any dose and frequency so you can see the tradeoff.
Can I get off tirzepatide and maintain weight?
SURMOUNT-4 data showed weight regain after stopping tirzepatide [6]. A low-dose maintenance schedule is one strategy some clinicians use for the long term while limiting side effects and cost. Gradual tapering under physician supervision is generally preferred over stopping abruptly.
How do I get off tirzepatide without gaining weight?
Gradual dose reduction rather than abrupt discontinuation is the standard approach. Some clinicians use a low-dose maintenance schedule to preserve metabolic benefits during a taper. Diet and exercise running in parallel improve long-term weight maintenance after the drug. Your prescriber should plan the taper.
Can I quit tirzepatide cold turkey?
Abrupt discontinuation is not dangerous the way stopping some medications is, but SURMOUNT-4 showed significant weight regain without a tapering strategy [6]. Most clinicians recommend gradual dose reduction so the body can adjust and lifestyle habits can take over. Discuss any stop plan with your prescriber first.
Plan Your Tirzepatide Schedule
Enter any dose, split frequency, and vial concentration. The free calculator returns peak, trough, and steady-state levels across your full schedule.
Open Tirzepatide Calculator →References
- Jastreboff AM, Aronne LJ, Ahmad NN, et al. Tirzepatide Once Weekly for the Treatment of Obesity (SURMOUNT-1). N Engl J Med. 2022;387(3):205-216. NEJM
- U.S. Food and Drug Administration. Zepbound (tirzepatide) Prescribing Information. NDA 217806. 2023. FDA Label
- U.S. Food and Drug Administration. Mounjaro (tirzepatide) Prescribing Information. NDA 215866. 2022. FDA Label
- Rosenstock J, Wysham C, Frías JP, et al. Efficacy and safety of a novel dual GIP and GLP-1 receptor agonist tirzepatide in patients with type 2 diabetes (SURPASS-1). Lancet. 2021;398(10295):143-155. PubMed
- Frias JP, Davies MJ, Rosenstock J, et al. Tirzepatide versus Semaglutide Once Weekly in Patients with Type 2 Diabetes (SURPASS-2). N Engl J Med. 2021;385(6):503-515. PubMed
- Aronne LJ, Sattar N, Horn DB, et al. Continued Treatment With Tirzepatide for Maintenance of Weight Reduction in Adults With Obesity (SURMOUNT-4): A Randomized Clinical Trial. JAMA. 2024;331(1):38-48. doi:10.1001/jama.2023.24945. PubMed
Keep Reading
Microdosing Tirzepatide Guide
The full evidence-based protocol with pharmacokinetic modeling behind this chart.
Tirzepatide Dosage Chart
The standard, non-split Mounjaro and Zepbound titration chart.
Tirzepatide Dosing Guide
The full standard protocol and clinical-trial detail for comparison.
Tirzepatide Side Effects
Managing the GI symptoms that are the main reason people microdose.
Compounded Tirzepatide
Where the vials used for most microdosing approaches come from.
Microdosing GLP-1 Medications
The cross-compound split-dose overview hub.
Medical Disclaimer: This chart is for informational and reference purposes only. It does not constitute medical advice, diagnosis, or treatment. Split-dose and sub-2.5mg microdosing of tirzepatide have not been studied in clinical trials and are off-label. GLP3 Planner does not endorse any specific dosing regimen outside FDA-approved protocols. Always consult a qualified healthcare provider before starting, changing, or adjusting any medication. Individual responses vary, and what works for one person may be harmful to another.